
Shah's Gastro, Cancer & Robotic Surgery Centre · Ahmedabad & Gandhinagar
The assessment that comes before the resection is planned: a staging laparoscopy, a washing of the abdominal lining, and the findings that move the answer away from surgery. Apollo Hospital, Bhat, Gandhinagar · Gota OPD, Ahmedabad.
Before any decision about how much stomach to remove, one question has to be settled: will removing it help. For gastric cancer that question is not answered by a CT scan alone. It is answered by a short keyhole operation — a staging laparoscopy with a washing of the abdominal lining — which looks directly at surfaces a scan cannot resolve. Where that look is clean, the resection is planned. Where it is not, an operation to remove the stomach would take away months of life and give nothing back. This page is about how Dr Harsh Shah reaches that decision, what would change it, and what a patient should ask before consenting to anything.

Shah’s Gastro, Cancer & Robotic Surgery Centre. Qualified in surgical gastroenterology specifically — a super-specialty training in the gastrointestinal tract rather than general surgery with an interest in it. The stomach, food pipe, pancreas and bowel are the whole of the practice, week after week, which is what makes a judgement about resectability worth taking.
Dr Harsh Shah
MS, MCh (Surgical Gastroenterology), DrNB (Surgical Gastroenterology)
Stomach Cancer Surgeon · Apollo Hospital, Bhat, Gandhinagar · Gota OPD, Ahmedabad
Google rating 4.89 from 216 reviews at the Gota clinic, and 4.94 from 17 reviews at Apollo, Bhat.
The decision about whether to operate is not a decision one surgeon makes alone. Every case that is not obviously metastatic is discussed at a tumour board — surgeon, medical oncologist, radiation oncologist, radiologist and pathologist in one room — before treatment starts. A curative plan made outside that discussion is one of the few things that should prompt you to seek another opinion, and it is worth asking whether your case was discussed there.
A stomach cancer is worth removing when the disease is confined to the stomach and the lymph nodes that drain it. It is not worth removing when cancer cells have already seeded the lining of the abdomen, when there are deposits in the liver or lungs, or when the tumour has grown into a major blood vessel that cannot be reconstructed. The difficulty is that the first of those — seeding of the abdominal lining — is the one a CT scan misses most often.
Patients arrive having been told two opposite things by two competent doctors, and assume one of them must be careless. Usually neither is. A CT scan resolves a deposit of a centimetre but not specks scattered across the peritoneum, and stomach cancer spreads in exactly that pattern — so a scan can read as operable when the abdomen is not, and the only honest way to close that gap is to look.
| What is being assessed | How it is assessed, and what it changes |
|---|---|
| Deposits on the lining of the abdomen (peritoneal disease) | Staging laparoscopy with washings, because a CT is unreliable here. Visible deposits, or cancer cells in the washing fluid, move the plan away from immediate resection |
| Spread to the liver or lungs | CT of chest, abdomen and pelvis in arterial and portovenous phases. Deposits outside the stomach and its nodes mean the disease is treated with drug therapy rather than an operation |
| Growth into neighbouring structures | CT, and direct assessment at laparoscopy. Involvement of the pancreas or a major vessel does not automatically rule out surgery, but it changes who should operate and whether chemotherapy comes first |
| Whether the patient can withstand it | Performance status, nutrition, haemoglobin, albumin, kidney and liver function. A gastrectomy on a malnourished patient is a different operation from the same gastrectomy on a prepared one |
| Biology of the tumour | HER2, PD-L1 and mismatch-repair testing on the biopsy. These do not decide resectability, but they decide what drug treatment is available — and that must be known before the first cycle, not after |
What that means in practice: a plan that says only “gastrectomy” has skipped a step. A plan worth consenting to says which of the five rows above have been checked, what each showed, and what the finding is that would change the answer.
A staging laparoscopy is a short keyhole procedure under anaesthesia through two or three small ports. The surgeon inspects the lining of the abdomen, the surface of the liver, the pelvis and the omentum directly, and washes the abdominal cavity with fluid that is then sent to the pathologist to look for cancer cells. Cells in the washing fluid are treated as equivalent to distant spread, even where nothing was visible to the eye.
It is offered where the tumour has grown beyond the most superficial layer of the stomach wall, or where lymph nodes appear involved, and a curative plan is being considered. It is not a formality and it is not the operation itself — most patients go home the same day or the next, and the resection, if one is appropriate, is a separate admission.
The reason it matters is worth stating without softening. A patient whose abdomen has already been seeded, and who undergoes a gastrectomy anyway, spends several weeks recovering from major surgery, loses the window in which drug treatment could have started, and gains nothing from the operation. A staging laparoscopy costs one day and one anaesthetic to prevent that. Where it is clean, everyone proceeds with more confidence, and the family has been told the truth about the abdomen rather than an inference from a scan.
Dr Harsh Shah has written on the evidence behind this for referring physicians: see the role of staging laparoscopy in gastric cancer.
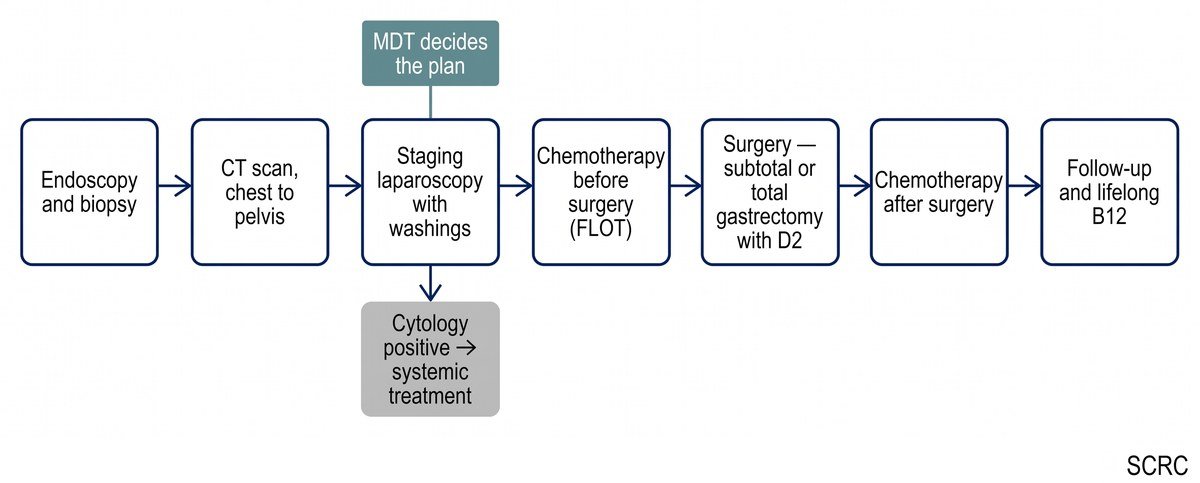
The order is not arbitrary. Endoscopy with adequate biopsies comes first and must record distances; the staging CT follows; biomarkers are sent on the biopsy material so the results are back before any drug is given; the staging laparoscopy is done last, once everything cheaper has been exhausted; and nutrition is assessed alongside all of it rather than at the end.
| Step | What it must produce |
|---|---|
| Endoscopy with biopsies | At least six biopsies from the edge of the ulcer or mass, and the distance in centimetres from the tumour to the junction with the food pipe and to the pylorus. Those two distances are what later decide how much stomach can be kept |
| CT chest, abdomen and pelvis | Two contrast phases. Read for spread outside the stomach, for nodes, and for involvement of neighbouring structures and vessels |
| Blood work and nutrition screen | Counts, kidney and liver function, albumin, tumour markers, and a formal nutrition score. Weight loss over ten per cent in six months, a low body mass index, a low albumin or poor intake all trigger a dietitian and prehabilitation before anything else |
| Biomarkers on the biopsy | HER2, PD-L1 and mismatch-repair or microsatellite testing, with Claudin-18.2 where it is available. Ordered early, because a result that arrives after the first cycle of chemotherapy has arrived too late to be used |
| Staging laparoscopy with washings | Direct inspection and cytology of the abdominal lining, for tumours beyond the superficial layers or with involved nodes where cure is the aim |
| Additional imaging, selectively | Endoscopic ultrasound only where it would change the decision, and a PET scan only where there is a specific question. Neither is routine, and neither should delay the pathway |
Where a tumour is blocking the outlet of the stomach and the patient cannot eat, a feeding tube into the small bowel is placed or a stent passed, so that nourishment never becomes the reason chemotherapy stops halfway.
Where cancer cells are found in the abdominal washings, where there are deposits on the peritoneum, or where the disease has spread to the liver or lungs, removing the stomach does not extend life. Treatment then leads with drug therapy chosen on the tumour’s own biology, with surgery reserved for a specific problem such as bleeding or blockage, and with symptom control and nutrition started at the same time rather than later.
This is the hardest conversation in the clinic and it is often handled badly elsewhere, in one of two directions. Patients are told “nothing can be done”, which is untrue — modern drug treatment for gastric cancer is selected on HER2 status, on PD-L1 expression and on mismatch-repair status, and the difference between treatments chosen that way and treatment chosen blindly is substantial. Or they are offered an operation because an operation feels like action. Neither serves the patient.
What is true is narrower and more useful. The stomach is removed when removing it changes the course of the illness. Where it does not, the operation is declined for the patient’s benefit, not withheld from them — and the reasoning is explained to the family in full, with the imaging and the cytology report in front of them. A small number of patients whose disease responds unusually well to drug treatment are reassessed later and become candidates for surgery at that point; that reassessment is a tumour board decision, not a promise made at the first visit.
Where the assessment is clean, the resection is a subtotal or a total gastrectomy depending on where the tumour sits and how far it is from the junction with the food pipe, always with a D2 lymph node dissection, and usually with chemotherapy before and after surgery for anything that has reached the muscle layer or the nodes.
One point about that plan belongs here rather than on the pages about the operations themselves, because it follows directly from the assessment: the node dissection is part of the operation and not an optional extra, and at least fifteen nodes must reach the pathologist. A thin node count makes the stage unreliable, and an unreliable stage makes every decision after surgery unreliable too.
How much stomach stays, the measurement that decides it, and how the approach is chosen are covered on the pages about the individual operations. For the overview of stomach cancer surgery at this practice, see stomach cancer treatment; for how the robotic platform is used across the gastrointestinal tract, see robotic surgery.
Dr Harsh Shah performs the staging laparoscopy himself and performs the resection himself, open, laparoscopically or robotically as the tumour dictates. The consultant who inspects your abdomen is the consultant who explains what was found, and the consultant who later reads your histology report with you.
That continuity is not a courtesy. A staging laparoscopy is a judgement made by eye in the moment — whether a nodule on the peritoneum is disease or scar, whether a plane is involved or merely adherent — and the value of that judgement depends on the experience of the person making it and on their being the same person who will act on it. A report written by one surgeon and acted on by another loses exactly the information that made the look worth doing.
For the resection that may follow, the approach follows the tumour, and a surgeon who tells you in advance what would make him open rather than keyhole is telling you something useful about how he works.
Consent for a staging laparoscopy and consent for a gastrectomy are two different conversations and should not be merged into one signature. The first covers a short procedure and the possibility of an answer nobody wants; the second covers a major operation, every complication by name, and a permanent change in how you eat.
For the gastrectomy, the complications that must be named to you, by name, are: bleeding needing a transfusion; infection at the operation site; a clot in the leg or in the lung; a cardiac event; a complication of anaesthesia; a leak from the join between the stomach or food pipe and the bowel; a blowout of the duodenal stump; delayed emptying of the stomach that remains; dumping — weakness, sweating or palpitations after a sweet or milky meal; bile reflux; an internal hernia years afterwards; and long-term vitamin B12 and iron deficiency. Conversion from a keyhole approach to open surgery belongs in the same conversation. A risk of death is part of every consent for a major gastrectomy and it is discussed with you personally, not left on a form.
The individual figures against each of those are given to you in writing at the consent discussion, worked out for your age, your fitness, your body mass index, whether you have had abdominal surgery before and whether you have had chemotherapy first. They are not published on a website, because a pooled average from a published series is not a prediction about you, and presenting one as though it were would be dishonest.
Six questions worth asking any surgeon before consenting to stomach cancer surgery:
A second opinion is most worth taking when you have been told the cancer cannot be operated on, when an operation has been offered without a staging laparoscopy in a tumour that warrants one, when a curative plan was made without a tumour board, or when two doctors have proposed different treatments.
Bring the endoscopy report and the endoscopy images if you have them; the biopsy report naming the type; the CT films on a disc or a drive rather than only the typed report; any PET report; any staging laparoscopy or cytology report; recent blood counts and albumin; a list of current medicines; and the weight at diagnosis alongside the weight today. That last pair is not a formality — the trend in weight tells a surgeon something no single scan does.
★★★★★
“We are very thankful to Dr. Harsh Shah for treating and operating on my father for gastric (stomach) cancer. From the first consultation to the surgery and follow-up, he guided us with great care and explained everything clearly. My father is doing well now, and we are extremely grateful for the treatment and support provided by Dr. Harsh Shah and his team. He is a highly experienced and compassionate doctor. We would definitely recommend Dr. Harsh Shah to anyone looking for an experienced doctor for stomach cancer treatment. Thank you, Doctor, for everything!”
Moh. Ahsan — Google review, Dr Harsh Shah – Robotic GI Surgeon, Apollo Hospital, Bhat
★★★★★
“My father has carcinoma of stomach ,Harsh sir did radical gastrectomy and he is recovering very nicely under Dr.Harsh's observation ,he listen each and every complain calmly and with patience and make patient very comfortable during treatment , during procedure and during stay at hospital. we are satisfied with the treatment and very confident about the fully recovery of disease as we are under treatment of Dr.Harsh & team.Thank you Dr.Harsh & his whole team and staff.”
tina parmar — Google review, Dr Harsh Shah, Gota, Ahmedabad
★★★★★
“Dr Harsh shah's dedication and commitment to his patients health are commendable. He always provides comprehensive explanations and ensures that we understood our treatment plans.Dr harsh shah is best stomach cancer surgeon in Ahmedabad Gujarat. Thank u so much sir for all support and help.🙏”
Haresh Chavda — Google review, Dr Harsh Shah, Gota, Ahmedabad
These are unedited Google reviews from Dr Harsh Shah’s own listings, reproduced word for word, including the original spelling.
A staging laparoscopy and a gastrectomy are costed separately, because they are separate admissions and one may make the other unnecessary. The estimate for either is given in writing before admission.
What moves the estimate for the resection: subtotal against total gastrectomy; open, laparoscopic or robotic; the room category; the number of nights; whether intensive care is required; and whether a feeding tube or a stent was needed beforehand. Chemotherapy is costed separately by the medical oncology team.
Apollo Hospital, Bhat is empanelled with the major insurers and with government schemes, and admissions are cashless wherever the policy allows; pre-authorisation is applied for before admission and the office prepares that paperwork. Bring the policy document and card, photo identification, all previous reports and films, the current medicine list, and the name of a family member who will stay through the admission.
Because a CT reliably shows a deposit of a centimetre and stomach cancer often seeds the lining of the abdomen in specks far smaller than that. The laparoscopy looks directly and washes the cavity for cells. It is the only way to know before committing you to a major operation.
It is treated as spread, because the outcome after a gastrectomy in that situation follows the cytology rather than the appearance. It changes the order of treatment: drug therapy leads, and surgery is reconsidered only if the disease responds unusually well.
No. It is a day-case procedure that fits inside the time the biomarker results take to come back, and it prevents the much longer delay of recovering from an operation that should not have been done.
Inoperable is not the same as untreatable. Treatment is chosen on HER2, PD-L1 and mismatch-repair status, and those results should be in hand. If they have not been sent, that is a reason to ask — and a reason a second opinion may be worth taking.
Yes. Where the outlet is blocked and a resection is not appropriate, a bypass, a stent or a feeding tube relieves the obstruction and restores nutrition. That is a real operation with a real purpose, and it is not the same as a cancer resection.
Shah’s Gastro, Cancer & Robotic Surgery Centre — Gota, Ahmedabad
Consultations, review of reports, follow-up and surveillance.
Google: Dr Harsh Shah · 4.89 from 216 reviews
Directions to the Gota clinic
Apollo Hospital — Bhat, Gandhinagar
Admission, surgery and inpatient care.
Google: Dr Harsh Shah – Robotic GI Surgeon · 4.94 from 17 reviews
Directions to Apollo, Bhat
Patients travel to Ahmedabad for stomach cancer surgery from across Gujarat — Gandhinagar, Mehsana, Nadiad, Anand, Bhavnagar, Rajkot, Jamnagar and Kutch — and from southern Rajasthan and western Madhya Pradesh. Send reports ahead on WhatsApp and the first visit can be a decision rather than a triage.
More on Dr Harsh Shah’s work in gastrointestinal cancer: stomach cancer treatment · food pipe cancer treatment.
Swasth Parivar: twice a month, practical advice on recovery, diet and warning signs. No advertising. Stop any time.
Your number is used for these updates and for the clinic to reach you. It is never sold or passed on. To stop, reply STOP on WhatsApp.
